
Sep 2
IPC Education for Low-Literacy and Diverse Workforces: Plain-Language IPC Training to Diverse Aged Care Teams
What is plain-language IPC training?
Plain-language IPC training uses clear words, visual aids, demonstrations, and practical examples to
help all workers understand infection prevention and control requirements regardless of literacy
level, learning style, or first language.
help all workers understand infection prevention and control requirements regardless of literacy
level, learning style, or first language.
Why does it matter?
Every worker in a residential aged care facility (RACF), whether they're a registered nurse, a
personal care worker, a cleaner, or a kitchen hand, has a role to play in preventing the spread of
infections. But a training program only works if the people in it understand what's being asked of
them.
The aged care workforce in Australia and New Zealand is among the most linguistically diverse in
both countries.(Source: AIHW, 2021; Department of Health Aged Care Workforce
Census, 2020) Many staff members speak English as a second, third, or even fourth language.
Health literacy - the ability to find, understand, and use health information - varies widely, even
among staff who are fluent in English. When IPC training relies on dense policy language, lengthy
written modules, or fast-paced verbal instruction, those who need the information most are often
the least able to absorb it.
This isn't a training gap that resolves itself over time. It's a design problem that needs a design
solution.
Who Makes Up a Diverse Aged Care Workforce?
A typical facility team might include workers who trained overseas and are still building their
confidence in English, workers who left school early and find written text hard going, younger staff
who learn best through video and demonstration, and older staff who prefer face-to-face instruction
to learning on a screen. Rostering adds another layer; night-shift, casual, and agency staff often
miss training sessions scheduled around a standard nine-to-five day.
None of this means these workers are any less capable or committed. It means a single, text-heavy training module cannot realistically reach everyone. Facilities that recognise this and adapt their approach see better outcomes on the floor: correct PPE use, consistent hand hygiene, and staff who feel confident raising concerns.
None of this means these workers are any less capable or committed. It means a single, text-heavy training module cannot realistically reach everyone. Facilities that recognise this and adapt their approach see better outcomes on the floor: correct PPE use, consistent hand hygiene, and staff who feel confident raising concerns.

What Does Low Health Literacy Mean for Infection Control Training?
Low health literacy doesn't only affect people with limited English. A worker can be a fluent English
speaker and still struggle with clinical terminology, dense paragraphs, or abstract instructions such
as "maintain standard precautions at all times." Training that assumes a particular reading level,
prior clinical knowledge, or cultural context will leave gaps, and those gaps show up exactly where
they matter most: at the bedside, in the sluice room, and during an outbreak.
The goal isn't to simplify the clinical content itself. Standard precautions, transmission-based precautions, and outbreak procedures still need to be followed precisely. The goal is to change how that content is taught, so understanding - not just attendance - is the measure of success.
The goal isn't to simplify the clinical content itself. Standard precautions, transmission-based precautions, and outbreak procedures still need to be followed precisely. The goal is to change how that content is taught, so understanding - not just attendance - is the measure of success.
How Can Facilities Make IPC Training Accessible to Everyone?
A few practical changes to training methods can make a real difference.
- Use plain language, not clinical shorthand: Replace "don PPE prior to entering the room" with "put on your gloves, gown, and mask before you go in." Define acronyms the first time they're used and keep sentences short.
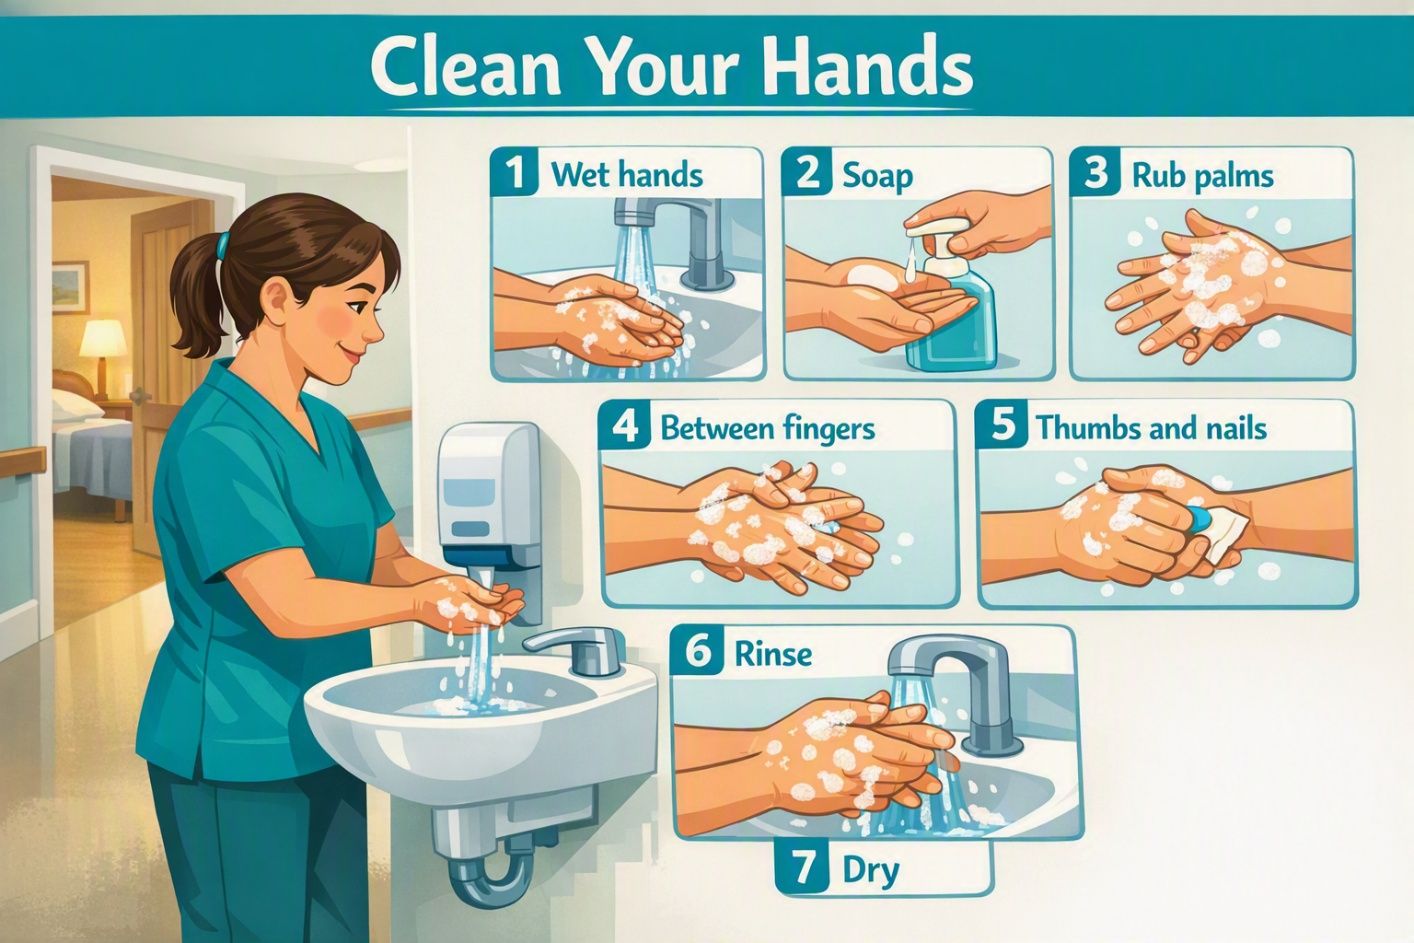
- Lean on visuals over text. Step-by-step images of hand hygiene, PPE donning and doffing, or waste disposal communicate more quickly and reliably than a paragraph of instructions - and they work regardless of a worker's first language.
- Use the teach-back method. Rather than asking "Does everyone understand?", ask a worker to show or explain the steps back to you. Teach-back reveals real gaps in understanding, not just polite nods in a training room.

- Offer more than one format. Short demonstration videos, one-page visual Flipcharts kept at the point of care, and small-group, hands-on sessions all reach people that a single written module misses.
- Translate key resources where practical. Even a translated one-page hand hygiene guide, placed next to the English version at a handwashing station, sends a clear message: this matters, and it's for everyone.
- Repeat and reinforce. One onboarding session is never enough. Short refreshers, spot audits with feedback, and visual reminders in staff areas keep IPC front of mind long after initial training.
What Role Do Managers Play in Supporting Inclusive IPC Education?
Facility managers set the tone. When management schedules training across all shifts - not just during business hours - casual and night staff stop missing out. When managers model good practice, staff see that IPC isn't a box-ticking exercise reserved for audits. And when managers back their IPC Lead's push for accessible resources, that Lead has the support needed to change how training is delivered, not just what it covers.
Managers should also ensure training materials are accessible for staff with differing literacy levels, language backgrounds, and learning preferences. Accessible education is a workforce capability issue, not an individual staff issue.
This approach also supports compliance. Under the Strengthened Aged Care Quality Standards (effective 1 November 2025), — and Ngā Paerewa (NZS 8134:2021) in New Zealand — facilities must demonstrate that all workers, regardless of role, are competent in infection prevention and control; competence must be demonstrated, not assumed. Accessible, teach-back-based training provides facilities with real evidence of understanding, not just a signed attendance sheet.
Managers should also ensure training materials are accessible for staff with differing literacy levels, language backgrounds, and learning preferences. Accessible education is a workforce capability issue, not an individual staff issue.
This approach also supports compliance. Under the Strengthened Aged Care Quality Standards (effective 1 November 2025), — and Ngā Paerewa (NZS 8134:2021) in New Zealand — facilities must demonstrate that all workers, regardless of role, are competent in infection prevention and control; competence must be demonstrated, not assumed. Accessible, teach-back-based training provides facilities with real evidence of understanding, not just a signed attendance sheet.

How Does IPS Support Facilities with Diverse Teams?
IPS builds resources with this challenge in mind. Flipcharts give staff a quick, visual, point-of-care reference for the steps that matter most, without a wall of text to wade through. The HUB brings policies, procedures, and audit tools together in one place so that IPC Leads can pull the right resource for the right shift or the right learner. TiNA helps facilities pinpoint individual training needs so that support can be targeted rather than generic. And in-person training brings a trainer into the room to demonstrate, answer questions, and use teach-back directly with staff - the format that reaches workers a written module never will.
Frequently Asked Questions
Why does plain-language IPC training matter for aged care teams?
Training only protects residents if staff actually understand it - dense clinical language and lengthy written modules leave gaps for workers with lower literacy or limited English.
What does low health literacy mean for infection control training?
It means some workers struggle with clinical terminology or abstract instructions even when fluent in English, so training needs to change how content is taught, not simplify the clinical standard itself.
How can facilities make IPC training accessible to everyone?
By using plain language, visual step-by-step aids, the teach-back method, multiple training formats, translated key resources, and regular refreshers across all shifts.
How does IPS support facilities with diverse teams?
Flipcharts for point-of-care visual reference, the HUB for centralised policies and resources, TiNA to identify individual training needs, and in-person training delivered directly to staff.
Take-Home Message
A diverse, varied-literacy workforce isn't a barrier to strong infection control - it's a reason to train differently. Plain language, visual tools, teach-back, and repetition turn IPC training from a compliance exercise into something every worker, in every role, can genuinely use.
Read more of our blogs on the IPS website, the HUB.
For a regular snippet of news, we are on LinkedIn and Facebook. Like us and share the post with others
For a regular snippet of news, we are on LinkedIn and Facebook. Like us and share the post with others
For a quick question, ask EVE, our multilingual bot or to contact us, email support@infectioncontrol.care

Lyndon Forrest
Managing Director | CEO
Lyndon is the Managing Director of Infection Prevention Services (IPS), bringing over 30 years' experience supporting aged care providers across Australia and New Zealand.
With a background spanning outbreak response, compliance, and infection risk management — alongside hands-on experience leading teams, managing multi-site operations, and navigating business turnaround — he understands both the clinical and organisational pressures aged care providers face. Lyndon holds a Master of Commerce (Industrial Relations), and applies that foundation to the people, process, and growth challenges that come with running a complex healthcare services business.
He is passionate about building the systems and capability that make infection prevention sustainable — not just compliant — and about helping organisations grow their confidence alongside their practice.
Lyndon's focus is straightforward: strengthen operations, develop the right people, and drive proactive infection prevention strategies that protect residents, staff, and communities for the long term.
Lyndon is the Managing Director of Infection Prevention Services (IPS), bringing over 30 years' experience supporting aged care providers across Australia and New Zealand.
With a background spanning outbreak response, compliance, and infection risk management — alongside hands-on experience leading teams, managing multi-site operations, and navigating business turnaround — he understands both the clinical and organisational pressures aged care providers face. Lyndon holds a Master of Commerce (Industrial Relations), and applies that foundation to the people, process, and growth challenges that come with running a complex healthcare services business.
He is passionate about building the systems and capability that make infection prevention sustainable — not just compliant — and about helping organisations grow their confidence alongside their practice.
Lyndon's focus is straightforward: strengthen operations, develop the right people, and drive proactive infection prevention strategies that protect residents, staff, and communities for the long term.
Erica Callaghan
Marketing Manager
Erica Callaghan is a dedicated professional with a rich background in agriculture and nutrient management. Growing up on her family's farm in Mid Canterbury, she developed a deep passion for farming. She currently resides on her partner's arable property in South Canterbury.
In 2017, Erica joined the Farm Sustainability team, focusing on nutrient management and environmental stewardship. In February 2024, she became the Manager of Marketing and Sales at Bug Control New Zealand - Infection Prevention Services, where her passion now includes improving infection prevention outcomes.
Outside of work, Erica loves cooking and traveling, often combining her culinary interests with her explorations in Italy and Vietnam. She enjoys entertaining family and friends and remains actively involved in farm activities, especially during harvest season.
Erica Callaghan is a dedicated professional with a rich background in agriculture and nutrient management. Growing up on her family's farm in Mid Canterbury, she developed a deep passion for farming. She currently resides on her partner's arable property in South Canterbury.
In 2017, Erica joined the Farm Sustainability team, focusing on nutrient management and environmental stewardship. In February 2024, she became the Manager of Marketing and Sales at Bug Control New Zealand - Infection Prevention Services, where her passion now includes improving infection prevention outcomes.
Outside of work, Erica loves cooking and traveling, often combining her culinary interests with her explorations in Italy and Vietnam. She enjoys entertaining family and friends and remains actively involved in farm activities, especially during harvest season.
Toni Sherriff
Clinical Nurse Specialist
Toni is a Registered Nurse with extensive experience in Infection Prevention and Control. Her career began as a kitchen hand and caregiver in Aged Care facilities, followed by earning a Bachelor of Nursing.
Toni has significant experience, having worked in Brisbane’s Infectious Diseases ward before returning home to New Zealand, where she continued her career as a Clinical Nurse Specialist in Infection Prevention and Control within Te Whatu Ora (Health NZ).
Toni brings her expertise and dedication to our team, which is instrumental in providing top-tier infection prevention solutions to our clients.
Toni is a Registered Nurse with extensive experience in Infection Prevention and Control. Her career began as a kitchen hand and caregiver in Aged Care facilities, followed by earning a Bachelor of Nursing.
Toni has significant experience, having worked in Brisbane’s Infectious Diseases ward before returning home to New Zealand, where she continued her career as a Clinical Nurse Specialist in Infection Prevention and Control within Te Whatu Ora (Health NZ).
Toni brings her expertise and dedication to our team, which is instrumental in providing top-tier infection prevention solutions to our clients.
Julie Hadfield
Accounts & Payroll
Julie is experienced in Accounts & Payroll Administration & after a long career in both the Financial & Local Government Sectors, is now working with our team. Julie brings her strong time management & organisational skills to our team, which is important to keep the company running in the background to enable the rest of our team to provide top notch service to all of our clients.
Julie is experienced in Accounts & Payroll Administration & after a long career in both the Financial & Local Government Sectors, is now working with our team. Julie brings her strong time management & organisational skills to our team, which is important to keep the company running in the background to enable the rest of our team to provide top notch service to all of our clients.
Andrea Murray
Content Editor
I attended Otago University in NZ and graduated as a Dental Surgeon. After 40 years in the profession, I retired in 2022. Infection prevention knowledge was part of everyday practice, dealing with sterilisation, hand hygiene, and cleaning.
Before retiring, I began doing some editing and proofreading for Bug Control as I am interested in the subject and in the English language. During the COVID-19 lockdown, I attended the ACIPC course "Introduction to Infection Prevention and Control", which increased my interest in the subject. I now work part-time as the Content Editor for the company.
I attended Otago University in NZ and graduated as a Dental Surgeon. After 40 years in the profession, I retired in 2022. Infection prevention knowledge was part of everyday practice, dealing with sterilisation, hand hygiene, and cleaning.
Before retiring, I began doing some editing and proofreading for Bug Control as I am interested in the subject and in the English language. During the COVID-19 lockdown, I attended the ACIPC course "Introduction to Infection Prevention and Control", which increased my interest in the subject. I now work part-time as the Content Editor for the company.
Personally, I lived in the UK for 10 years. My two children were born in Scotland, and now both are living in Europe, one in Amsterdam, Netherlands, and the other in Edinburgh, Scotland. I live close to Fairlie on the South Island of NZ, a beautiful part of the country, and I love being out of the city.
Princess
Customer Support
Princess began her career as a dedicated Customer Service Representative, honing her communication and problem-solving skills. She later transitioned into a Literary Specialist role, where she developed a keen eye for detail. Her journey then led her to a Sales Specialist position, where she excelled in client relations.
Now, as a Customer Support professional in Infection Prevention Services. Princess focuses on ensuring customer satisfaction, building loyalty, and enhancing the overall customer journey.
Princess began her career as a dedicated Customer Service Representative, honing her communication and problem-solving skills. She later transitioned into a Literary Specialist role, where she developed a keen eye for detail. Her journey then led her to a Sales Specialist position, where she excelled in client relations.
Now, as a Customer Support professional in Infection Prevention Services. Princess focuses on ensuring customer satisfaction, building loyalty, and enhancing the overall customer journey.
Dianne Newey
Senior Infection Prevention and Control Consultant
Dianne is a Senior Clinical Consultant at Infection Prevention Services (IPS), bringing over 35 years of nursing experience and a depth of clinical knowledge that most people would need two careers to accumulate.
Having served as Clinical Director at Royal Ryde Rehabilitation Hospital alongside a career spanning the full breadth of clinical practice, Dianne has seen it all — and more importantly, knows exactly what to do about it. She is the person in the room that everyone quietly hopes will speak first.
For more than seven years she has been a cornerstone of the IPS team, providing clinical advice, developing and reviewing policies and procedures, delivering monthly IPC webinars to IP Leads, and conducting environmental audits in aged care facilities across Australia and New Zealand. If infection prevention has a question, Dianne almost certainly has the answer — and she'll deliver it with a laugh that you'll hear from the other end of the corridor.
A true fountain of knowledge, wrapped in the kind of warmth and humour that only three decades of nursing can produce. Customers don't just trust Dianne — they look forward to hearing from her.
Dianne is a Senior Clinical Consultant at Infection Prevention Services (IPS), bringing over 35 years of nursing experience and a depth of clinical knowledge that most people would need two careers to accumulate.
Having served as Clinical Director at Royal Ryde Rehabilitation Hospital alongside a career spanning the full breadth of clinical practice, Dianne has seen it all — and more importantly, knows exactly what to do about it. She is the person in the room that everyone quietly hopes will speak first.
For more than seven years she has been a cornerstone of the IPS team, providing clinical advice, developing and reviewing policies and procedures, delivering monthly IPC webinars to IP Leads, and conducting environmental audits in aged care facilities across Australia and New Zealand. If infection prevention has a question, Dianne almost certainly has the answer — and she'll deliver it with a laugh that you'll hear from the other end of the corridor.
A true fountain of knowledge, wrapped in the kind of warmth and humour that only three decades of nursing can produce. Customers don't just trust Dianne — they look forward to hearing from her.
Caoimhe (Keva) Stewart
Clinical & Business Operations Manager
Caoimhe is the Clinical & Business Operations Manager at Infection Prevention Services (IPS), bringing a clinical background as a Registered Nurse across the UK and Australia — and an almost unsettling ability to make technology do exactly what she wants.
With experience in Occupational Health, Palliative Care, and Community Nursing, she understands the real challenges faced by healthcare teams. What she may lack in stature she more than makes up for in impact — Caoimhe is the kind of person who walks into a problem, sizes it up, and has three solutions before anyone else has finished reading the brief.
Customers love her. Not just because she delivers — though she always does — but because she genuinely cares about the outcome on the other side. She is passionate about creating seamless learning experiences and empowering organisations with the tools, knowledge, and support needed to strengthen infection prevention practices and improve care outcomes.
Small in size. Mighty in results. Completely irreplaceable.
Caoimhe is the Clinical & Business Operations Manager at Infection Prevention Services (IPS), bringing a clinical background as a Registered Nurse across the UK and Australia — and an almost unsettling ability to make technology do exactly what she wants.
With experience in Occupational Health, Palliative Care, and Community Nursing, she understands the real challenges faced by healthcare teams. What she may lack in stature she more than makes up for in impact — Caoimhe is the kind of person who walks into a problem, sizes it up, and has three solutions before anyone else has finished reading the brief.
Customers love her. Not just because she delivers — though she always does — but because she genuinely cares about the outcome on the other side. She is passionate about creating seamless learning experiences and empowering organisations with the tools, knowledge, and support needed to strengthen infection prevention practices and improve care outcomes.
Small in size. Mighty in results. Completely irreplaceable.
Bridgette Mackie
Clinical Nurse Educator
Bridgette is an experienced New Zealand Registered Nurse, qualified Healthcare Auditor, and Healthcare Educator with a strong background in clinical quality, competency assessment, and infection prevention. She has led large-scale OSCE and CAP training programmes for internationally qualified nurses, developed sector-specific educational resources, and coordinated HealthCERT audit preparation in the surgical sector.
Known for her engaging teaching style and genuine passion for supporting learners, Bridgette excels at making complex topics accessible and relevant. She blends operational leadership with a deep commitment to professional development and safe, effective practice.
Bridgette is an experienced New Zealand Registered Nurse, qualified Healthcare Auditor, and Healthcare Educator with a strong background in clinical quality, competency assessment, and infection prevention. She has led large-scale OSCE and CAP training programmes for internationally qualified nurses, developed sector-specific educational resources, and coordinated HealthCERT audit preparation in the surgical sector.
Known for her engaging teaching style and genuine passion for supporting learners, Bridgette excels at making complex topics accessible and relevant. She blends operational leadership with a deep commitment to professional development and safe, effective practice.
